How to Choose the Right Cervical Interbody Fusion Cage?

Choosing the right cervical interbody fusion cage is not a simple product comparison. It is a clinical decision shaped by anatomy, pathology, surgical approach, bone quality, and the patient’s daily demands. A cage that fits one patient may create problems in another. The difference can be measured in millimeters, yet those millimeters influence alignment, stability, and nerve decompression.

Dr. K. Daniel Riew, a widely recognized cervical spine surgeon, has expressed a central surgical principle: “The goal of surgery is to decompress the spinal cord and nerve roots.” Cage selection must support that goal, not distract from it. Surgeons typically assess cage height, footprint, lordotic angle, material, graft space, and resistance to subsidence. A cage should contact strong endplate bone, rather than rest too deeply on the weaker central endplate. Small details matter. So does imaging.

This guide examines how these factors affect cervical interbody fusion outcomes. It considers single-level and multilevel procedures, alignment restoration, radiographic fusion, and practical insertion challenges. It also explains why “more lordosis” is not automatically better. Patient-specific judgment remains essential. There is no universally superior cage. Even experienced surgeons may weigh the same evidence differently. That uncertainty deserves honesty, not marketing language.

The discussion will also address implant design, bone graft options, and potential complications, including subsidence, migration, and nonunion. Evidence can guide a choice, but it cannot replace careful planning, informed consent, and surgeon expertise. In real practice, the best cage is the one that safely matches the patient’s anatomy and the operation’s biological and mechanical goals.
How to Choose the Right Cervical Interbody Fusion Cage?

Understand the Purpose and Types of Cervical Interbody Fusion Cages

How to Choose the Right Cervical Interbody Fusion Cage?

Understand the Purpose and Types of Cervical Interbody Fusion Cages

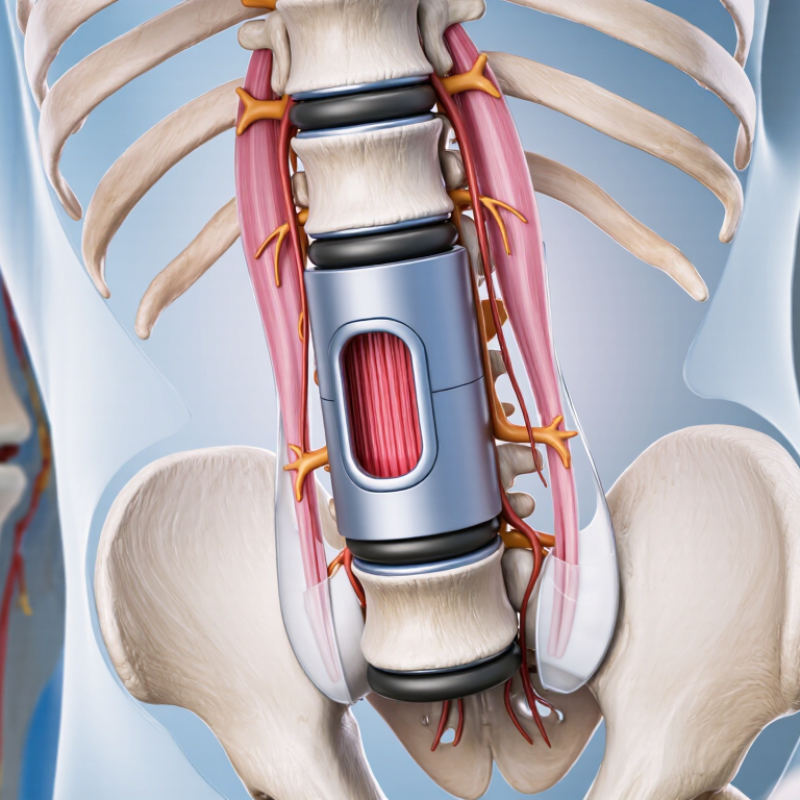
A cervical interbody fusion cage replaces a damaged disc space after decompression. It supports vertebral height, helps restore alignment, and creates a chamber for bone fusion. The AHRQ HCUP Statistical Brief No. 233 reported a 67% rise in U.S. spinal fusion hospitalizations from 2000 to 2015. That growth makes careful selection more important, not automatic. The cage is a tool, not the operation itself.

Static cages provide fixed height and are widely used for predictable disc-space restoration. Expandable cages can adjust height during surgery, but overexpansion may increase endplate stress. Stand-alone designs reduce anterior hardware, while cage-and-plate constructs may improve immediate stability. Materials also differ. PEEK offers radiolucent imaging, while porous titanium may support bone attachment. Peer-reviewed comparative reviews report broadly similar fusion results across several anterior constructs, but subsidence and swallowing symptoms still vary. The evidence is not perfectly uniform.

Tips: Match cage height to the patient’s endplates, not a template. Review bone quality, alignment, surgical level, and imaging needs. Ask how the design manages graft material and migration risk. A 2023 NASS evidence review emphasizes patient selection and surgeon judgment. No cage fits every anatomy. That detail deserves more attention.

Assess Patient Anatomy, Diagnosis, and Surgical Requirements

How to Choose the Right Cervical Interbody Fusion Cage?

Patient anatomy should guide cage selection, not convenience. A 2023 AHRQ HCUP analysis reported that cervical spinal fusion procedures rose from about 174,000 in 1998 to 334,000 in 2011. More procedures increase the need for disciplined planning.

Start with the diagnosis. MRI can show disc herniation, cord compression, and foraminal narrowing. CT helps assess osteophytes, endplate shape, and bone quality. Standing radiographs reveal cervical alignment and segmental instability.

A cage that restores lordosis may suit a kyphotic segment, while excessive height can over-distract the disc space. Fit matters. Measure twice.

Surgical requirements also change the decision. For one level, footprint and endplate contact may dominate. Multilevel reconstruction demands stronger alignment control and predictable load sharing. Consider the approach, available disc-space height, graft volume, fixation strategy, and the surgeon’s access angle.

The smallest cage is not automatically safer. The largest is not automatically stronger. A 2011 AHRQ HCUP report also found cervical fusion patients becoming older over time, reinforcing the need to assess osteoporosis and endplate integrity rather than relying on age alone. NASS guidance supports correlating imaging with symptoms and neurological findings. That correlation can be imperfect. Recheck the plan when anatomy, diagnosis, and symptoms disagree.

Compare Cage Materials, Designs, and Structural Features

How to Choose the Right Cervical Interbody Fusion Cage?

Material and design should match the patient, not marketing language. PEEK is radiolucent, so surgeons can monitor bone bridging clearly on follow-up imaging. However, its lower surface integration may require careful endplate preparation and graft selection. Titanium offers strong bone contact, while porous titanium can support bone ingrowth through its open structure. A 2023 systematic review in the European Spine Journal reported that subsidence rates vary widely across cervical cage studies, often because implant design, endplate quality, and surgical technique differ.

The cage’s structure matters just as much. A wider footprint may distribute load across stronger endplate zones. An appropriate lordotic angle can help restore disc height and cervical alignment. Teeth or anti-migration features may improve stability, but aggressive fixation can damage fragile bone. Large graft windows are useful, although excessive void space may reduce mechanical support. The FDA’s device guidance and post-market surveillance data also show why imaging follow-up remains important. Laboratory strength is not the whole clinical story. I would not select a cage from material alone. That approach sounds simple, but it is incomplete.

Tips: Check the endplates carefully. Avoid over-distraction. Compare the cage footprint with the patient’s anatomy. Review radiographs for settling, alignment, and fusion progression. Published evidence is helpful, but it is not perfect. Surgical judgment still matters.

How to Choose the Right Cervical Interbody Fusion Cage? — Compare Cage Materials, Designs, and Structural Features
Comparative reference table for anterior cervical interbody fusion (ACDF) cage selection. Values are typical material or design characteristics; exact performance depends on implant geometry, surgical technique, bone quality, fixation, and patient anatomy.
Comparison Dimension Option / Typical Specification Relevant Data or Structural Characteristic Potential Advantages Trade-Offs and Selection Considerations
Cage material PEEK Polyetheretherketone Elastic modulus is approximately 3–4 GPa, substantially lower than titanium alloy. Radiolucent on standard radiographs, so radiopaque markers are commonly incorporated. Produces limited imaging artifact; allows assessment of the fusion bed and graft region. Its stiffness is closer to bone than that of solid metal. Untreated PEEK is relatively bioinert and does not inherently provide a bone-bonding surface. Surface treatment or an appropriate graft strategy may be used when clinically indicated.
Cage material Titanium alloy Solid titanium Elastic modulus is approximately 100–115 GPa, much higher than typical cortical bone. Highly radiopaque and visible on radiographs and CT. High strength, established biocompatibility, and clear implant visibility. Surface texture can support mechanical interlock with bone. High stiffness may increase stress concentration at the endplates in some constructs. Metal artifact can make evaluation of the fusion area more difficult than with radiolucent materials.
Cage material Porous titanium Additively manufactured or sintered structure Contains interconnected pores; effective stiffness depends on porosity, strut design, and manufacturing method rather than bulk titanium alone. Porous architecture may support bone ingrowth and improve biological fixation when pore size, connectivity, and surface quality are appropriately controlled. More complex manufacturing and imaging characteristics. Porosity does not guarantee fusion; adequate endplate preparation, stability, and graft biology remain essential.
Cage material Carbon-fiber reinforced polymer Radiolucent polymer matrix reinforced with carbon fibers; mechanical properties vary with fiber orientation and fiber volume. Low imaging artifact and the ability to monitor the fusion region with comparatively limited obstruction. Less commonly selected than PEEK or titanium in many current cervical systems. Device-specific mechanical data and long-term clinical evidence should be reviewed.
Material surface Uncoated polymer surface Provides a stable structural platform but generally has limited intrinsic osteoconductivity. Predictable manufacturing and low radiographic artifact. May require a well-prepared graft-filled central chamber and secure fixation to promote stable fusion.
Material surface Porous or roughened osteoconductive surface Increases surface area and may provide mechanical interlocking for bone ongrowth or ingrowth. Potentially improves biological fixation compared with a smooth surface, particularly when the architecture is designed for bone integration. Surface architecture must be balanced with strength, particle control, manufacturability, and the risk of excessive endplate interaction.
Cage footprint Broad medial-lateral and anteroposterior footprint Distributes load over a larger endplate area and reduces dependence on a small contact zone. Can improve construct stability and may reduce focal endplate stress and subsidence risk when the implant fits the patient’s anatomy. An oversized footprint may damage the endplate or be difficult to insert. The footprint should remain within the vertebral endplate margins.
Cage height Patient-specific restored disc height Common cervical cage heights are often approximately 4–10 mm, but available sizes vary by level, anatomy, and implant system. Appropriate height can help restore disc-space height, foraminal dimensions, and segmental alignment. Over-distraction may cause endplate injury, postoperative pain, or facet loading. Height should be selected from imaging and intraoperative trialing rather than by a fixed value.
Sagittal profile Lordotic cage angle Many cervical systems offer multiple angles, commonly within approximately 5–15 degrees; the exact range is device-specific. May help restore or maintain segmental cervical lordosis and reduce the need for excessive anterior plate contouring. Excessive focal angulation can create uneven endplate contact or affect adjacent-level alignment. Segmental and overall cervical alignment should both be considered.
Graft chamber Central or large graft window Creates space for autograft, allograft, or another legally indicated bone-graft material. Window size and internal support columns vary by design. Provides a visible fusion bed and can increase the volume of graft material placed within the cage. A very large window may reduce structural support if the cage is not adequately reinforced. Graft containment and resistance to migration are important.
Endplate interface Teeth, ridges, serrations, or textured contact surfaces Mechanical features are designed to resist anterior-posterior migration and improve initial grip on the endplates. May improve primary stability, especially when combined with an appropriate footprint and supplemental fixation. Aggressive teeth or excessive impaction can injure the endplate. The interface should match bone quality and the surgeon’s preparation technique.
Fixation method Standalone cage with integrated screws or anchors Combines interbody support with direct fixation; fixation trajectory and locking mechanism vary by design. May reduce the need for a separate anterior plate and can provide additional resistance to migration and rotation. Requires careful attention to screw or anchor trajectory, local anatomy, construct stability, and the risk of hardware-related complications.
Fixation method Cage used with an anterior plate The cage provides interbody support while the plate and screws add anterior stabilization. Can improve resistance to migration and may be useful when additional stabilization is required. Introduces additional hardware and may increase the risk of postoperative dysphagia or soft-tissue irritation; profile and positioning are important.
Radiographic assessment Radiolucent body with radiopaque markers Markers identify cage position while the main cage body allows visualization of the graft and fusion region. Facilitates postoperative assessment of implant placement, disc-space height, and progressive fusion. Marker position must be understood correctly because it does not always represent the complete cage boundary. CT and radiographs may still be limited by other hardware.
Endplate preservation Controlled endplate preparation Removal of disc material and cartilage should preserve the strong subchondral bone supporting the cage. Maintains load-bearing capacity and may reduce the risk of cage subsidence. Insufficient preparation can limit fusion biology, while excessive preparation can weaken the endplate. The implant design cannot compensate for poor endplate preparation.
Patient and level factors Bone quality, operative level, alignment, and number of levels Low bone mineral density, small endplates, multilevel surgery, kyphosis, and revision procedures can change the mechanical requirements. Patient-specific selection improves the match between cage footprint, height, fixation strategy, and expected loading conditions. No single material or design is best for every patient. Imaging, bone-health assessment, and surgeon experience should guide the final choice.

Evaluate Implant Compatibility, Safety, and Clinical Evidence

How to Choose the Right Cervical Interbody Fusion Cage?

Evaluate Implant Compatibility, Safety, and Clinical Evidence

Choosing a cervical interbody fusion cage requires more than checking dimensions. The implant should match the patient’s anatomy, surgical approach, and imaging requirements. A surgeon should assess disc-space height, endplate shape, bone quality, and the amount of correction needed. The cage must also work with the available instruments and remain visible during fluoroscopy. MRI compatibility matters too, especially when long-term monitoring may be necessary.

Safety deserves practical attention. Review risks such as subsidence, migration, nonunion, implant breakage, and postoperative neurological complications. Endplate preparation is critical. Excessive removal can weaken bone and increase sinking risk. Poor sizing can create instability or unwanted pressure. No checklist is perfect. Patient factors, surgical technique, and follow-up quality can change outcomes significantly.

Clinical evidence should guide, not replace, professional judgment. Look for peer-reviewed studies with meaningful follow-up periods, clear patient-selection criteria, and reported complications. Fusion rates alone may not show whether pain, function, or alignment improved. Comparative studies can be useful, but their results may not apply to every patient. I would question evidence based on small samples, short observation periods, or vague definitions of success. Regulatory authorization and documented quality controls also support reliability, but they do not guarantee an ideal result for each individual.

How to Choose the Right Cervical Interbody Fusion Cage?

Evaluate implant compatibility, safety, and clinical evidence through elastic-modulus matching

The chart shows typical reported elastic-modulus ranges for materials relevant to cervical interbody fusion. A smaller stiffness mismatch with bone may help reduce stress shielding and subsidence risk, but material stiffness alone does not establish clinical superiority. Final selection should also consider MRI compatibility, radiographic visibility, endplate preparation, cage footprint, subsidence data, fusion outcomes, and patient-specific anatomy.

Sources: Kurtz SM, Devine JN. PEEK biomaterials in trauma, orthopedic, and spinal implants. Biomaterials. 2007;28:4845–4869. Rho JY, Ashman RB, Turner CH. Young’s modulus of trabecular and cortical bone material. Journal of Biomechanics. 1993;26:111–119. Values are representative published ranges and vary by test method, composition, and anatomical location.

Confirm Surgical Technique, Surgeon Expertise, and Follow-Up Needs

How to Choose the Right Cervical Interbody Fusion Cage?

Confirm Surgical Technique, Surgeon Expertise, and Follow-Up Needs

Choosing a cervical interbody fusion cage starts with the planned surgical technique. The approach, spinal level, bone quality, and alignment goals all matter. A cage suitable for one procedure may not suit another. Ask how the cage supports disc height and stability during the selected approach. The surgeon should also explain imaging findings in plain language. Small details matter, including implant size, endplate preparation, and protection of nearby nerves.

Surgeon expertise deserves equal attention. Ask how frequently the surgeon performs cervical fusion and manages difficult anatomy. Review their training, hospital resources, and complication-management experience. A qualified surgeon should discuss realistic benefits, possible risks, and reasonable alternatives. No checklist replaces judgment. I would also ask what might change during surgery if the anatomy differs from the scans.

Follow-up planning should be confirmed before the operation. Clarify the schedule for wound checks, neurological assessments, and imaging. Ask when driving, lifting, work, and exercise may resume. Recovery is not always predictable. Pain can improve slowly, and stiffness may persist longer than expected. A cage may appear well positioned, yet symptoms still require careful monitoring. Report worsening weakness, swallowing difficulty, breathing problems, fever, or drainage promptly. Do not rely only on online recovery timelines. Your follow-up plan should match your health, procedure, and daily responsibilities.